
If it feels as though your womb has dropped, arrange an appointment with your GP, ob-gyn or a pelvic-floor specialist. A vaginal bulge or dragging feeling can be pelvic organ prolapse, but an examination is needed to tell which structures are involved. You do not have to diagnose it yourself. If you suddenly cannot pee, seek emergency care now.
I would write down when the feeling started, whether you can empty your bladder, and what makes the pressure better or worse. That gives the clinician something more useful than a guessed stage. Until you’re assessed, avoid tasks that noticeably worsen the pressure and ask for help with heavy loads. A baby moving lower during pregnancy is a different meaning of “dropping”; new symptoms still belong in a conversation with your maternity team.
What “my womb dropped” can mean
Uterine prolapse means the uterus has moved downward into the vagina because its supporting tissues are not holding it in the usual position. The word “dropped” sounds like one dramatic event. In practice, support changes can develop gradually, and you might notice them during an ordinary bathroom visit or after a day on your feet.
A bulge is not always the uterus. The bladder can bulge against the front vaginal wall, called a cystocele. The rectum can bulge against the back wall, called a rectocele. More than one area can be involved. The ACOG anatomy explanations show why these conditions can feel similar even though they involve different structures.
I wouldn’t try to identify an organ from an online photograph. The useful observation is that something feels or looks different. A clinician can name it; you can explain how it affects standing, walking, using the toilet or having sex.
If you are pregnant and your bump looks lower, you may mean lightening, when the baby settles farther down into the pelvis. That is different from uterine prolapse and does not by itself tell you exactly when labor will start. Kaiser Permanente’s explanation of dropping during pregnancy makes that distinction. Do not use it to dismiss new vaginal tissue, bleeding, fluid loss or pain.
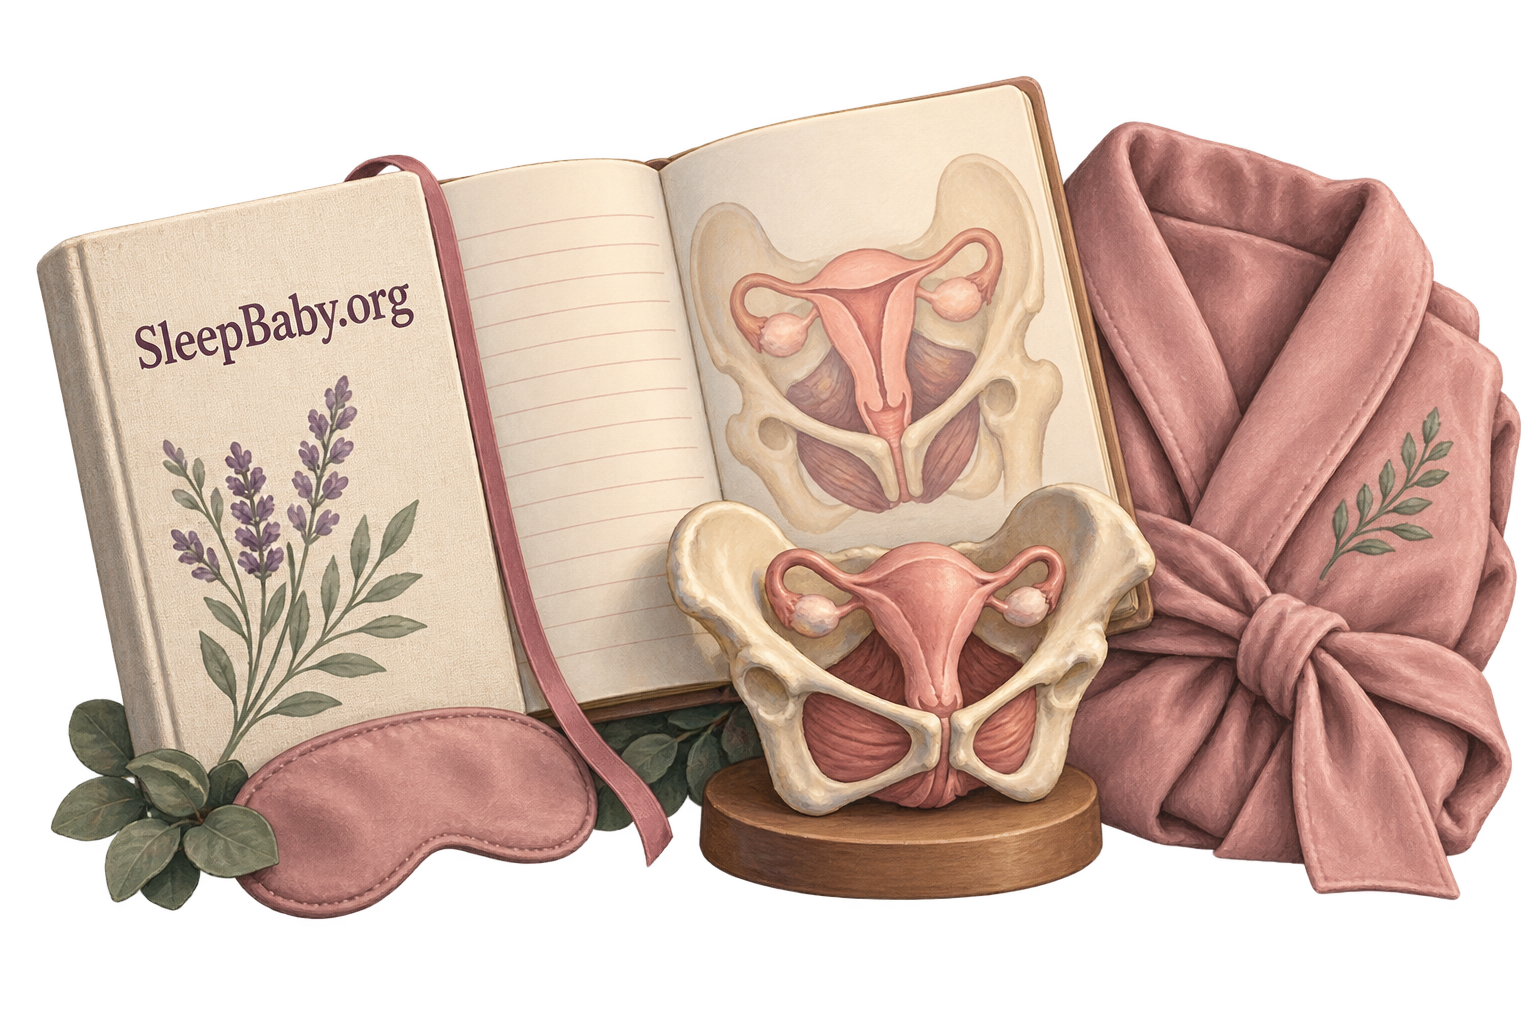
The details worth telling your clinician
Prolapse may cause a feeling of heaviness or dragging, tissue at the vaginal opening, difficulty emptying the bladder or bowel, urine leakage, or discomfort during sex. Some people have few symptoms. The NHS symptom guide recommends getting a vaginal lump or other possible prolapse symptoms checked.
Pressure can feel worse after standing for a long time and improve when you lie down. That pattern is described by RCOG, but it is not a home diagnostic test. Feeling better at bedtime does not prove the concern is imaginary, and a bad afternoon does not tell you that a particular stage has changed.
Keep your description ordinary. “I feel a bulge after carrying the washing upstairs” is useful. So is “I need to pee again straight after I’ve been.” You can mention pain, dryness, an unfamiliar sensation during sex, or needing extra effort to open your bowels without deciding which symptom belongs to which condition.
For the appointment, including symptoms you notice at night
Bring the observation and the question
- Pressure after standing or carrying
- Record the activity and whether resting changed it. Ask: “What should I change about lifting, work or exercise while we assess this?”
- A bulge, leakage or incomplete emptying
- Describe what happens without repeatedly examining yourself. Ask: “Which area is involved, and do my bladder or bowel symptoms need separate tests?”
- Discomfort affecting sleep, closeness or baby care
- Name the task you have stopped or dread doing. Ask: “Which treatment could help this particular problem, and when will we review it?”
SleepBaby.org • Conversation prompts, not a diagnostic score
Why it can happen after birth, or much later
Pregnancy and childbirth can affect the muscles, nerves and connective tissues supporting the pelvic organs. Vaginal birth is a risk factor, but having had a cesarean does not make pelvic-floor symptoms impossible. Pregnancy itself changes the demands on those tissues. Mayo Clinic explains these pregnancy and birth effects.
Aging, menopause, ongoing constipation, persistent coughing and other sources of strain can also contribute. There may be more than one factor. I would not turn this into an investigation of the one grocery bag you should supposedly never have picked up. A risk factor helps guide care; it is not a verdict on how carefully you gave birth or recovered.
Tell the clinician about previous births, pelvic operations, constipation, coughing and any earlier pelvic-floor treatment. If your symptoms started years after childbirth, that history is still relevant. If you have never given birth, you still deserve an assessment rather than being told this cannot be prolapse.
What the appointment and a stage number can tell you
Your clinician will ask about symptoms and may recommend a pelvic examination, sometimes using a speculum. You may be examined lying down or standing. Ask for an explanation before each part, a chaperone, or a pause whenever you need one. Mention pain or anxiety about the examination before it begins.
A stage describes how far the prolapse descends on examination. It does not describe your worth, your effort, or every part of your quality of life. I’d ask for the name of the prolapse and its stage in writing, along with the proposed next step. Those three details are easier to remember than an unfamiliar string of medical terms.
If the examination does not match what you notice later in the day, say so. You can explain when the bulge appears, which position makes it more noticeable and what the symptom stops you doing. That is useful follow-up information. It is not a reason to strain repeatedly at home to reproduce a photograph.
Bladder symptoms may lead to a urine test, a scan to check emptying, or other testing. Ask which question each test is meant to answer. Prolapse and another problem can coexist, so a diagnosis should not become a reason to overlook new bleeding, infection symptoms or pain.
Treatment does not have to start with surgery
There is no single treatment everyone with a “dropped womb” needs. The decision takes account of what is prolapsing, how much it bothers you, your health, and your plans for pregnancy or sex. If symptoms are absent or not troublesome, monitoring may be reasonable. That should include knowing when to return, rather than simply being left to manage alone.
For symptoms that disrupt daily life, ask about the nonsurgical options as well as an operation. I’d bring one concrete goal: getting through a work shift, walking to the park comfortably, emptying your bladder more easily, or feeling less worried about intimacy. A plan becomes easier to judge when you know what improvement you are looking for.
Pelvic-floor physiotherapy: technique before more repetitions
Pelvic-floor muscle training can be part of treatment, but “do more Kegels” is not a complete assessment. A trained professional can check contraction and relaxation, discomfort and your individual goals. NICE recommends tailored supervision and a course of at least four months for some symptomatic prolapses, depending on the examination findings.
Ask your therapist to check what you are doing, give you a manageable routine, and explain how to know whether you are bearing down instead of lifting. If an exercise hurts or increases pressure, stop and ask for an adjustment. Do not keep adding repetitions because an app says you have missed a target.
I’d also tell the therapist what a normal day contains. A plan designed around uninterrupted quiet time may need adapting when you feed a baby, commute or care for an older child. You can ask which part matters most on a difficult day and how progress will be reviewed. No exercise schedule should promise that every prolapse will disappear.

For the baby-care part of the evening
Make the next night handoff easier to explain
If you are also caring for a baby, deciding who handles the change, settling and return to the crib can take one practical task off your list. The SleepBaby.org Workshop includes Our Night Handoff and Caregiver Shift & Fatigue Plan among 15 guides, plus five audio tracks and the original Baby Sleep Miracle PDF.
You can explore the Baby Sleep Miracle presentation on SleepBaby.org before deciding. The current Workshop costs $9 USD once, with no subscription.
This is general baby-sleep education. It does not treat prolapse, prescribe lifting restrictions or replace pelvic-floor care, and sleep results are not guaranteed.
A fitted pessary can provide support
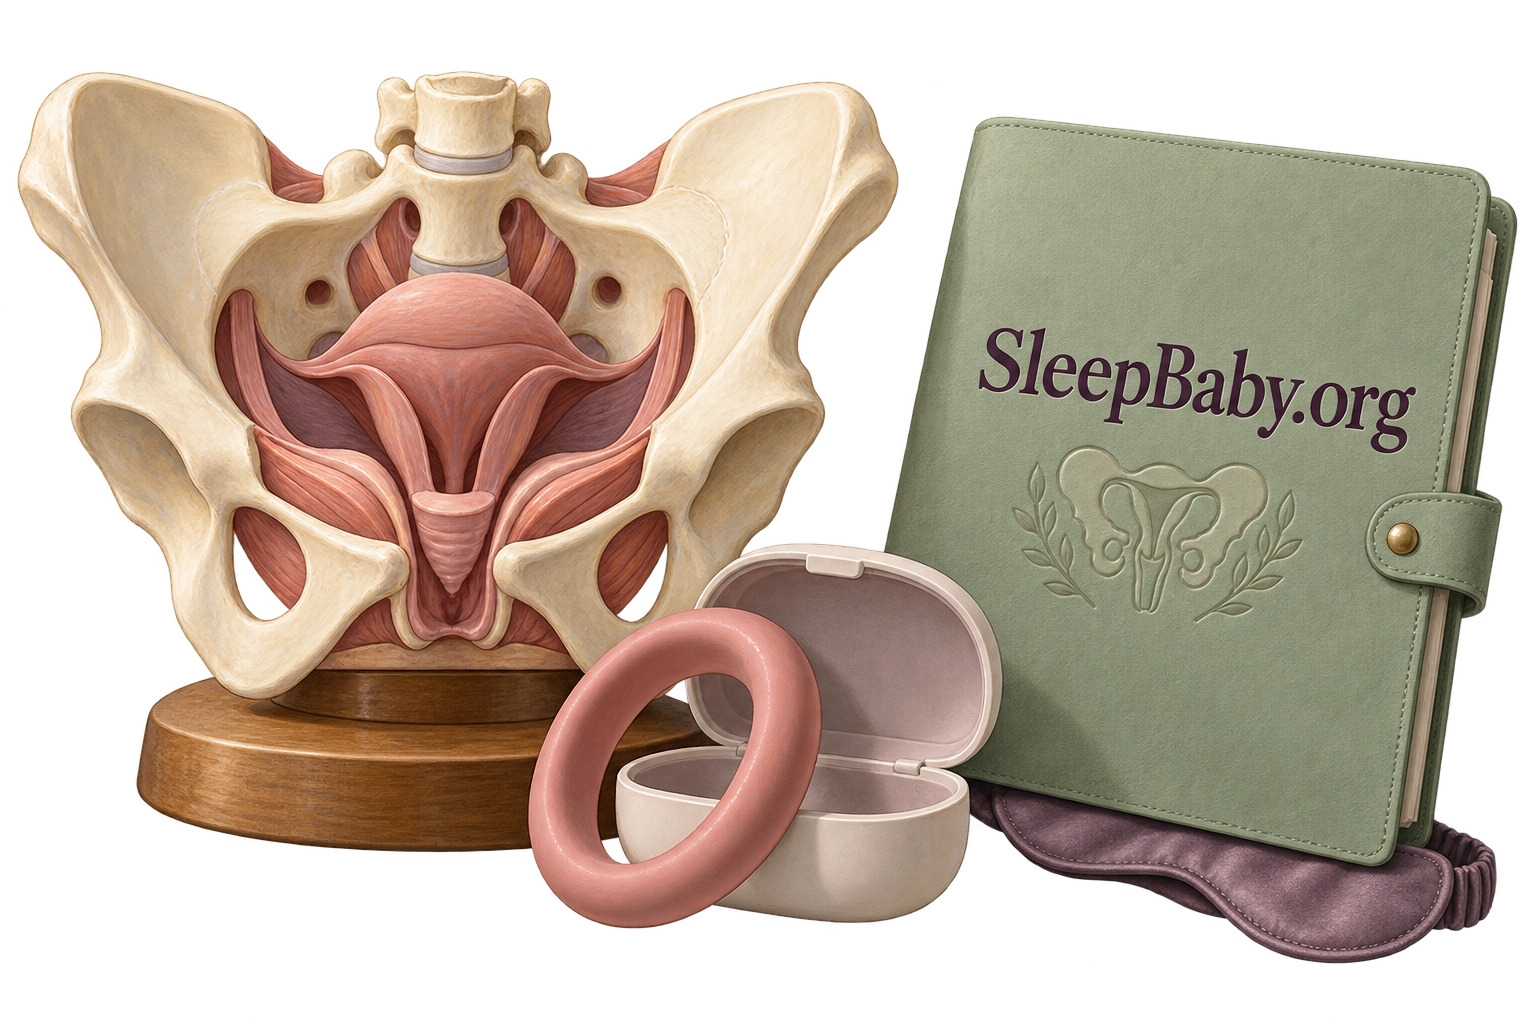
A pessary is a device placed in the vagina to support the prolapse. It is an option to discuss if you want nonsurgical help, are waiting for surgery or hope to become pregnant in the future. There are different shapes and sizes; the first fitting may not be the final fit.
Before leaving a fitting, ask what comfort should feel like, how the device is checked, and whom to contact if you have trouble peeing, pain, bleeding or troublesome discharge. Follow the clinic’s removal, cleaning and review plan. Some people are taught to manage their own pessary; that is different from ordering one and guessing how to fit it.
The Northern Care Alliance pessary guide explains fitting and follow-up. A pessary supports symptoms while used; it is not a guaranteed permanent repair. Whether it stays in for sex depends on the device and your care instructions.
Vaginal estrogen and surgery answer different questions
Vaginal estrogen may be offered for menopausal vaginal symptoms associated with prolapse. It is not a universal postpartum prescription or a way to lift the uterus permanently. Discuss your circumstances, including breastfeeding and any relevant medical history, before using hormonal treatment.
If surgery is being considered, ask which repair is proposed and why. Removing the uterus is not the only possible approach to uterine prolapse; uterus-preserving procedures exist. The RCOG treatment overview describes several options and their tradeoffs. Ask specifically about recurrence, bladder or bowel effects, sex, recovery, and whether mesh is involved. Availability and mesh rules differ by procedure and country.
Make future pregnancy plans part of that discussion early. You may be advised to delay an operation, and the choice should account for your wishes as well as the examination. A surgery consultation can be a chance to understand options; it does not obligate you to book a procedure that day.
If an operation does become your choice, plan the recovery before the date is set. Ask what the specific procedure means for carrying a child, driving, stairs, work and sex. Recovery instructions are not interchangeable between operations. A friend’s timeline may not apply to yours.
Then work through an ordinary weekday on paper. Who can bring the baby to you? Who can manage the toddler’s car-seat buckles and lift the stroller? Which commitments can move? Give the surgical team the gaps in that plan while there is still time to discuss support. Needing help after an operation is information for planning, not a reason to pretend you have a spare adult available.
What “avoid heavy lifting” looks like with a baby at home
This is where general advice can leave a parent stuck. You still have a child who needs feeding, a car seat and washing that does not carry itself. I would ask the clinician for task-specific guidance rather than a vague promise to “take it easy.” Is carrying your baby comfortable? Does lifting the car seat with the baby inside trigger pressure? Are repeated crib transfers the harder part?
Until you have an individual plan, reduce optional loads and stop activities that clearly worsen symptoms. Ask someone else to carry the loaded laundry basket, move groceries or lift the stroller into the car when help is available. This is practical load-sharing, not a universal weight limit. What is appropriate depends on your assessment, recovery and any recent surgery.
If you are parenting alone or help is limited, tell the clinician that directly. “Avoid lifting” cannot be the whole plan when you have no one to do the transfers. Ask about referral, equipment assessment where appropriate, and realistic adjustments. Do not alter crib rails or raise a mattress outside the manufacturer’s instructions to make reaching easier.
Keep the baby’s sleep surface firm, flat and clear, and place the baby on their back for sleep. An adult bed, sofa or recliner does not become a safe substitute because your pelvis is uncomfortable. The AAP safe-sleep guidance remains the starting point while you arrange help.

Constipation, movement and resting without making promises
Reducing constipation and straining is a useful part of prolapse care. Tell your clinician if you strain often, cannot empty properly, or need unusual maneuvers to pass stool. Discuss food, fluids and any medicines that might be contributing. If simple changes are not enough, ask about treatment rather than repeatedly forcing a bowel movement.
For activity, the question is what your body tolerates and what your care team recommends. High-impact exercise or heavy loads may need adapting. You do not have to decide that all movement is harmful or try to prove you can complete your old workout. Ask for a graded return that fits the activities you actually want to do.
Resting may ease pressure, but I would not promise that a particular sleeping position will reverse prolapse. Choose a comfortable position consistent with your pregnancy or postoperative advice, and report symptoms that keep waking you. A pillow arrangement can address comfort; it cannot replace an examination.
Notice function rather than checking the bulge every hour. Can you manage the same ordinary task more comfortably? Are toilet symptoms changing? Bring those observations to your follow-up. Progress does not have to mean the anatomy looks exactly as it did before pregnancy, and a difficult day does not give you a complete forecast.

Hear pelvic-floor therapists explain the options
UAMS Health shares this conversation with pelvic-floor therapists Morley Anderson and Destiny Caldwell. They explain the different structures involved, common symptoms and treatment choices. It is an overview, not a personalized exercise prescription.
The useful takeaway: describe the symptoms and ask about your options rather than assuming surgery is inevitable. You can watch the discussion on YouTube or read the hospital’s transcript. The guidance in this article remains usable without playback.
Sex, another pregnancy and the worry about “forever”
You can ask about sex even if it feels like an awkward detail beside the examination. Pain, reduced sensation, dryness or fear of making things worse are worth discussing. You do not have to push through pain to find out whether everything is working. Ask what is appropriate for your symptoms and, if you use a pessary, that specific device.
If you hope for another pregnancy, bring that wish into the first treatment conversation. Ask whether the current plan affects trying to conceive, how care would change during pregnancy, and who would advise on birth planning. An internet account of someone else’s prolapse cannot predict your pregnancy or tell you which delivery is right for you.
I would also separate “I have this diagnosis” from “I know exactly how my body will feel forever.” Symptoms can change, and treatment aims to improve how you feel and function. Nobody can promise a particular recovery date from a search phrase. You are allowed to ask for realistic expectations, a review date and a next option if the first plan is not enough.
If worry about your body is taking over sleep, relationships or the time you hoped to spend with your baby, tell a healthcare professional. Emotional support belongs alongside physical care. Our guide to recognizing postpartum depression and getting help may be useful if low mood or anxiety is also part of what you are experiencing.
Leave with a next step you can actually use
Before the appointment ends, I’d make sure you know who is responsible for the next step. If a referral is planned, ask how you will hear about it. If you are trying a treatment, ask when it will be reviewed and what should prompt an earlier call. If no treatment is recommended yet, ask what changes you should report.
Take the plan home in a form you can find again. A short note on your phone is enough: diagnosis, contact number, agreed activity changes and review date. You do not need a perfect symptom spreadsheet. The point is to avoid finding yourself at midnight trying to remember whether you were supposed to call back.
If the appointment is a long way off
Tell the referring team if symptoms change while you wait. A referral already being in the system does not mean you must keep new problems to yourself. Describe the change in function: you cannot empty your bladder as well, discomfort has increased, or the pressure is interfering with work or essential baby care. Ask whether the timing needs reassessment. Urgent warning signs still require urgent care.
If cost, transport or childcare makes an appointment difficult, ask what services or referral routes are available locally. It can help to check whether a first discussion can happen remotely, while understanding that an examination may still be needed. Ask the clinic what to bring and whether a support person or baby can attend, rather than discovering its policy at the door.
If the first plan is not helping enough
Bring the original goal back into the follow-up. Instead of deciding only that “physio failed,” explain which symptom changed, which stayed the same, and whether you could realistically follow the plan. If an exercise was painful, the instructions were unclear or the routine did not fit your day, that is information the therapist can work with.
Ask what would count as enough improvement, how long the current trial should continue, and what the next option would be. A treatment can help one problem without solving another. Less pressure does not automatically answer a separate emptying problem or pain during sex. You can ask for those concerns to be assessed in their own right.
I would finish that conversation by repeating the agreed next step in your own words. “I’ll try the adjusted plan until our review, and call sooner for these changes” is much more usable than leaving with a pile of instructions you are afraid to question.
If bleeding is a separate concern after birth, our guide to lochia and postpartum bleeding warning signs can help you distinguish the questions to raise. If ordinary baby bedtime is also difficult, finding a workable bedtime is a separate planning job. Neither should delay your own medical care.

An Amazon book option for the questions after your appointment
Why Did No One Tell Me? by Emma Brockwell, paperback. Penguin identifies Brockwell as a specialist women’s-health physiotherapist and describes this book as covering pelvic-floor care, birth recovery and returning to exercise.
Why I’d consider it: It may suit a parent who wants broader postpartum background to discuss with their clinician. I would choose an educational book over buying an internal exercise device without an assessment.
Check first: The linked paperback is ISBN 9781785043369. Confirm the author, edition and format. This is general reading, not a prolapse diagnosis or a prescription to follow every exercise.
Skip buying: Your clinician’s handouts, the free sources below or a library copy may give you what you need. You do not need this book to begin treatment.
As an Amazon Associate I earn from qualifying purchases.
Sources and references
- NHS: pelvic organ prolapse
- RCOG: assessment and treatment choices
- ACOG: prolapse anatomy
- NIDDK: urinary retention
- CDC: urgent maternal warning signs
- NICE NG210: supervised pelvic-floor care
- Northern Care Alliance: pessary care
- Mayo Clinic: the pelvic floor around birth
- Kaiser Permanente: lightening in pregnancy
- AAP: infant safe sleep
- UAMS Health: video and transcript
- Penguin: Emma Brockwell book details
After you have a plan for your own care
Let the next caregiver take a clear piece of the evening
You can need pelvic-floor care and still need ordinary help with the baby’s night. If you want a clearer way to organize settling and caregiver handoffs, explore the SleepBaby.org Workshop and decide whether its general sleep guidance fits your household. Your prolapse care stays with your healthcare team.






What viewers said10 comments · 4 replies+
Archived comments from the original Baby Sleep Miracle presentation. Not independently verified by SleepBaby.org; individual experiences vary.
Thank you so much for this video! I had no idea about the dangers of baby swings :O
Hi Mary-Ann. I have a question: Is method in any way similar to the ones recommended by Dr Bucknam, Dr. Weissbluth or Dr. Karp? We tried those but none of them help.
Hi Regina, thank you for your question. The short answer is no. The techniques I share in my guide are based on newest scientific research and this is why I have never seen any approach similar to the one I recommend.
This method really works! I tried it on my son Jesus and after just one week he went from waking up more than 5 times a night to waking up just once or twice. You are a lifesaver, Mary-Ann!
I'm truly impressed with how much information you share in your video. And all for free! I can feel that you truly care about mothers like myself, and that's hard to find these days. I have recommended your site to several of my friends already.
Mary-Ann, our child suffers from autism. Is your approach still suited?
Chloe, I made sure my method can be used with any child, even babies who are special like yours. Please note that I'm not a doctor and that I always advice to consult with your physician because nothing is more important than the safety and well-being of your love.
Hallo Mary-Ann, I'm from Germany. Do you have your guide in German?
Hello Heide, we do! Normally you should already see our video in German. If not, please contact our support so they can guide you
Thenk you for your answer, Mary-Ann!
I just completed your approach and I have to say, it worked almost too well. Yes, it took a bit of getting used to with your bedtime routine but the difference is huge. My son George used to take 1 hours to go down and now he's firmly asleep in no more than 10 minutes! You're the best!
It seems I'm the only man watching this video, lol! What you shared about the 'emotional backpack' made immediate sense to me and I can't wait to help my little girl Mila to unpack it!
Hey there, just discovered your site and this really sounds different. Just wanted to say thanks for sharing :)
For everyone who's still thinking about getting Mary-Ann's guide I want to advise you to go ahead. I wasn't sure myself but now I'm so thankful I invested in this program. It made a huge difference in our life as a family and yes, my baby girl does sleep through the night now.