
If your child seems to like pain, first check whether they are being injured. Enjoying strong movement or pressure, showing little reaction to a bump, and deliberately hurting themselves are different observations. None tells you a diagnosis by itself. I would stop anything unsafe, check their body, and ask what happened. Repeated injury, a sudden change, or intentional self-harm needs professional help, even when your child looks calm afterward.
Get help first if your child may be in danger
Call 911 in the U.S. for an immediate life-threatening situation, a serious injury, or imminent risk of suicide. Stay with your child if they say they are going to kill themselves. If you cannot keep them safe, seek emergency help now. Outside the U.S., use your local emergency number.
In the U.S., you or your child can call or text 988 for suicidal thoughts or an emotional crisis, including help deciding what to do next. You can call about someone you are worried about. A crisis line does not replace emergency medical care for a life-threatening injury. These are the NIMH help routes.
After a head impact, being hard to wake, a seizure, new weakness, or trouble walking or speaking warrants emergency care. Vomiting or other concerning symptoms need urgent medical advice. Use the head-injury guidance and your local care service; do not decide that an injury is harmless because your child barely cried.
If there is no immediate emergency but your child is deliberately hurting themselves or saying they want to, contact their pediatrician or mental-health clinician promptly. Tell the office what is happening and ask about urgency rather than waiting for the next routine checkup. The NHS recommends seeking support for self-harm and thoughts of self-harm, including treatment for injuries. You do not need to work out the reason before asking.

What do you mean when you say your child “likes pain”?
I would replace that phrase with one specific observation. “They ask for a firm hug” gives a clinician different information from “They keep injuring themselves when upset.” So does “They had a bruise but did not mention it.” The word pain can make these situations sound alike when the next step may be quite different.
They seek a strong sensation
Your child may like pushing, movement, or a particular kind of touch. Sensory seeking describes looking for input; it does not prove a wish to be injured. NHS occupational-therapy guidance describes both seeking input and noticing some sensations less readily. If the behavior is unsafe or disrupts everyday life, bring it to the pediatrician or occupational therapist. Read the sensory-pattern guidance.
They barely react when they get hurt
A small outward reaction does not show you how much pain your child feels. Look at the injury and changes in how they move, eat, play, or communicate. Do not pinch, press harder, or expose them to something hot or cold to “test” their pain tolerance. Tell the pediatrician if reduced responses are new, persistent, or linked with repeated injuries.
They hurt themselves during distress
The immediate job is to prevent injury and get appropriate help. Repeated self-injury may need assessment of physical discomfort, communication, the environment, and emotional health. You cannot settle the cause from the behavior alone. A child who has difficulty speaking still deserves a careful search for pain or illness.
They intentionally injure themselves to manage feelings
This needs a compassionate response and professional assessment. The American Academy of Pediatrics explains that self-injury can occur without an intention to die, but it is associated with suicide risk and should be taken seriously. Neither assume suicidal intent nor assume its absence. AAP guidance on children and teens who self-harm.
These descriptions can overlap. A sensory explanation does not make injury acceptable, and having sensory differences does not rule out emotional distress. I would give the clinician the actual behavior and your child’s words, without choosing a label for them first.
Could your child be responding to pain rather than enjoying it?
That possibility deserves attention, especially when the behavior starts suddenly. Check ordinary clues: a change in eating, an uncomfortable clothing seam, constipation, a recent illness, or a new way of holding part of the body. These are observations to report, not a diagnosis to make at home.
A Cerebra pain guide hosted by Children and Family Health Devon discusses children with severe intellectual disabilities or communication difficulties. It explains that pain can be hard to identify and may be associated with self-injury. It also cautions that the site of the self-injury does not reliably identify where the underlying pain is. That is a reason to ask for a medical assessment, not to assume every episode has the same explanation.
I would say exactly what changed: “Eating has become difficult, and this behavior started yesterday.” That gives the clinician something to investigate. “They are just sensory seeking” can accidentally close a question that still needs an answer.
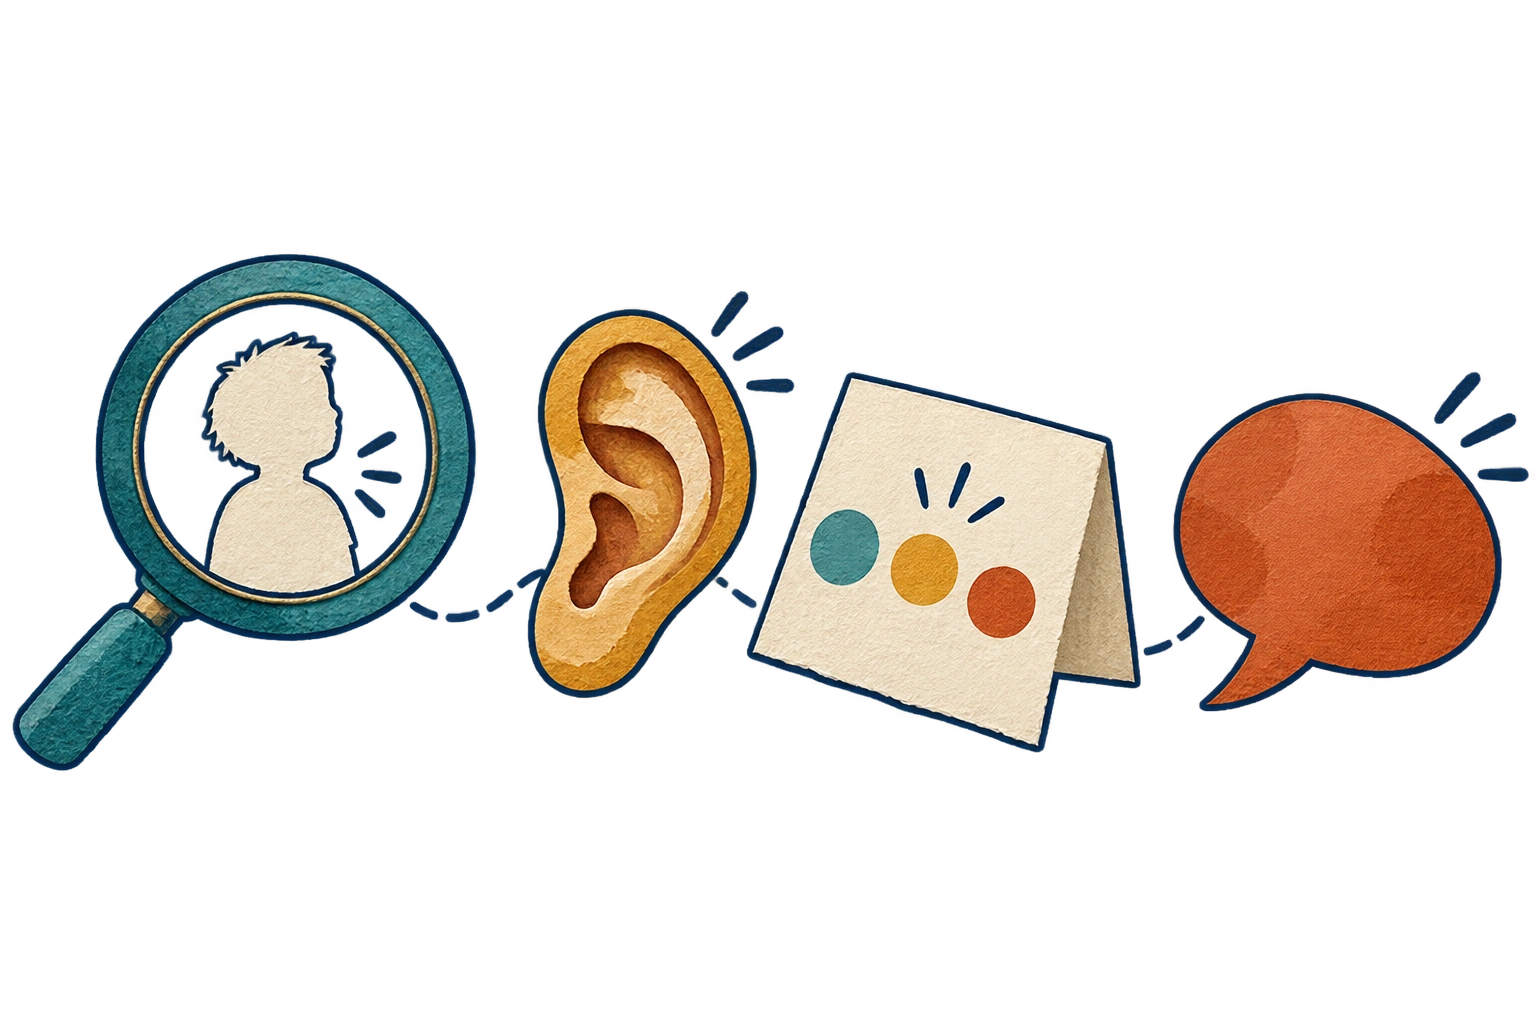
A way to organize what you notice
Body · Moment · Meaning
This is my note-taking aid for a conversation with your child’s clinician. It is not a screening test, a diagnosis, or permission to wait when your child needs help.
- Body: What needs attention?
- Record any visible injury, reported pain, or change in eating, movement, sleep, or usual behavior. Arrange care for the injury or concerning change.
- Moment: What was happening?
- Note the place, activity, noise, transition, and people present. Write what happened immediately before and afterward without guessing the motive.
- Meaning: What can your child tell you?
- Use their own words, gestures, or communication aid. “I don’t know” is useful information too. Do not fill the gap with an accusation or diagnosis.
Safety comes before completing the notes. If your child is in danger, put the notebook down and get help.

A useful note might read: “After the noisy school pickup, they repeatedly bumped into the sofa. I offered a quieter room. They chose to sit there.” That is a hypothetical example, not proof of a sensory cause. “They were trying to annoy me” is an interpretation and gives the next adult less to work with.
Keep the record brief and private. Write down an episode after everyone is safe; do not ask your child to recreate it or delay helping so you can film it. If the pattern is recurring, share the notes with their clinician and the appropriate school or childcare contact. The NHS describes the value of identifying triggers, early signs, and what follows a behavior, and advises calm intervention when someone is at risk.
A separate plan for ordinary bedtime
Give the evening one manageable starting point

Once urgent concerns are addressed, ordinary bedtime may still need some organization. You can try the free planning preview at SleepBaby.org for three choices and one suggested starting step, in your browser without a sign-up or card.
I would keep the bedtime notes separate from the record you bring to the pediatrician. One helps organize the evening; the other helps your care team understand a health or safety concern.
The optional paid SleepBaby.org Workshop offers short lessons you can revisit and a seven-night tracker. It is sleep-planning support, not treatment for sensory difficulties or self-harm, a suicide safety plan, or medical clearance to leave a child unmonitored. Follow your child’s care plan first.
What can you try when the issue appears to be sensory seeking?
First, address injury, possible pain, and any urgent concern. When your child is safe and the question is about everyday sensory preferences, start with one modest, voluntary change. I would choose something easy to stop and easy to describe to the occupational therapist.
Offer a choice, then watch the response
- If the room seems overwhelming: reduce unnecessary sound and offer a quieter space. Keep access to you available.
- If your child seeks pushing or movement: an age-appropriate, supervised activity such as gently pushing a small laundry basket may be an option. Keep the path clear, the load manageable, and the activity comfortable.
- If your child seeks hand pressure: they can choose to press their own palms together gently, if comfortable. Let them control it and stop when they want to.
The Chelsea and Westminster sensory advice includes environmental changes and everyday movement. Doncaster and Bassetlaw occupational-therapy advice includes self-directed palm pressure and allowing children control over pressure during personal care. These ideas require a fit with your child’s age, abilities, and care plan.

Judge the activity by your child’s response, not by how convincingly someone online calls it “calming.” Do they choose it? Can they stop? Does it remain comfortable? If it increases distress or causes pain, stop. Repeated unsafe behavior needs assessment even if an alternative works on some occasions.
I would skip painful “substitutes,” forced hugs, and any attempt to hold a child down or apply strong pressure without an individualized professional plan. You do not need to improvise a sensory treatment to take your concern seriously. A pediatric occupational therapist can help assess everyday participation and suitable activities; the pediatrician can address possible illness or injury alongside that work.
For a baby who is hitting their head or repeatedly injuring themselves, contact the pediatrician rather than adapting a school-age activity. Do not add pillows, bumpers, or loose padding to a crib to manage the behavior. Keep the sleep space consistent with NICHD safe-sleep guidance and ask for advice about the specific pattern.

How to talk when you are worried about self-harm
Choose a private moment when you can listen. You can be clear without demanding an explanation: “I noticed you’ve been getting hurt. Can you tell me what was happening?” If you think the injury was deliberate, ask plainly: “Have you been hurting yourself on purpose?” These are suggested openings, not a conversation you must perform perfectly.
If there are concerns about suicide, ask directly, “Are you thinking about suicide?” NIMH explains that asking does not increase suicidal thoughts or behavior. Listen without judgment, help reduce access to dangerous items, connect with professional or crisis support, and keep following up. Its five action steps are a useful starting point.
Keep the next sentence useful
If your child tells you: “Thank you for telling me. I want to help keep you safe, and we’ll get help with this.”
If they cannot explain: “You don’t have to find all the words right now. I’m here, and I’m going to ask someone who can help us.”
If they ask you to keep it secret: “I’ll respect your privacy as much as I can. I can’t keep a safety concern secret from people who need to help.”
If they do not want to talk to you: offer a conversation with their clinician or another appropriate trusted adult. You can still contact the clinician about your concerns.

Avoid insults, punishment, or arguing over whether the injury is “serious enough.” Ask what support feels possible. The NHS guidance for supporting someone who self-harms emphasizes understanding their emotions and avoiding judgment. You can take the behavior seriously while keeping your voice steady.
For a younger or nonspeaking child, use their usual communication supports and tell the clinician what you have observed. Do not treat an inability to answer a complex question as reassurance. Nor would I keep asking the same question in different ways until I got the answer I hoped for.
If your child reports that someone else is hurting or threatening them, treat that as a separate safety concern. Move toward protection and appropriate professional help; do not reinterpret their disclosure as a sensory preference.
Make the next appointment about the whole pattern
Bring your brief notes and explain the concern in the first sentence. I would want the appointment to cover injury or physical discomfort, the child’s communication and sensory needs, emotional distress, and what is happening at home or school. Different professionals may address different parts of that picture.
Questions worth taking with you
- Does this injury or change need treatment or another examination?
- What should we do during another episode, and what would make it an emergency?
- Which assessment fits: pediatric, developmental, occupational therapy, mental health, or more than one?
- How should school or childcare respond, and what information do they need?
- Who do we contact if things worsen before the next appointment?
When self-harm is involved, ask the clinician to help make a specific safety plan. It should address warning signs, supportive people, getting urgent help, and reducing access to dangerous items. The AAP’s guidance for parents concerned about suicide recommends professional support and a safer home environment. A promise that your child will stop is not a substitute for practical support.
Arrange the next contact before leaving if you can. “We will check in on Thursday, and this is the number to use sooner” is more usable than an open-ended instruction to keep an eye on things. If you are struggling to keep your child safe while waiting, seek urgent help instead of simply waiting for a referral.
A short AAP video for parents concerned about teen self-harm
The American Academy of Pediatrics’ Why Do Teens Self-Harm and What Can Parents Do About It? is about 1 minute 53 seconds. Its focus is adolescent self-harm, not diagnosing a toddler’s sensory behavior. It discusses parental support and planning actions to keep a young person safe.
If you cannot watch: respond without blame, seek professional assessment, and make a concrete safety plan with the care team. Use the emergency and crisis routes above whenever needed. The AAP’s written companion article provides the parent guidance.
An optional drawing supply for a quieter conversation
For a child who likes drawing, paper and crayons can offer another way to show what happened or how they feel. I would offer them without asking for a particular picture. Let your child tell you what the drawing means; do not diagnose feelings from a color or a shape.
Crayola Large Crayons, 16 count, item 520336 are an optional choice if you need supplies. The manufacturer lists them for ages 3 and up and describes a larger size for developing grips. They are ordinary art materials, not a treatment, a self-harm prevention tool, or a reason to postpone care.
Use age-appropriate supervision, put broken pieces away, and skip this option if your child mouths materials or their care plan makes it unsuitable. You can use a safe drawing supply you already own, or invite your child to talk, point, or use their usual communication aid. Buying something is not a necessary step.
As an Amazon Associate, I earn from qualifying purchases.
Find this exact crayon set on Amazon
The link opens an Amazon search for the named set. Match the 16-count Large Crayons and item number; listings, prices, and availability may change.

What about bedtime tonight?
Use the safety or medical plan first. A child who becomes quiet or sleepy has not thereby been assessed, and an easier bedtime does not establish why an injury happened. Follow the clinician’s advice about supervision, injury care, and when to seek help again.
For an otherwise safe, ordinary evening, I would keep the routine familiar and leave room for connection: the usual wash, comfortable clothes, a story or quiet conversation, and a clear next step. Avoid turning the last ten minutes of the day into an investigation or a test of a new sensory gadget. If touch helps your child, ask what they want rather than assuming.
You can note bedtime alongside other observations for the clinician without making sleep responsible for everything. Your most useful next step may be a phone call, a medical check, a quieter transition, or listening to one more sentence. Choose that step from what is happening now.
Sources
- American Academy of Pediatrics: When Children and Teens Self-Harm
- NIMH: Frequently Asked Questions About Suicide
- NIMH: Five Action Steps to Help Someone Having Thoughts of Suicide
- Chelsea and Westminster NHS: Sensory Processing Difficulties
- NHS: Responding to Challenging Behaviour in Children
- NHS: Where to Get Help for Self-Harm
- NHS: How to Help Someone Else Who Self-Harms
- Cerebra: Pain, a Guide for Parents (hosted by Children and Family Health Devon)
- NHS: Head Injury and Concussion
- Crayola: Large Crayons, 16 Count, Item 520336
- Doncaster and Bassetlaw NHS: Children’s Occupational Therapy Sensory Advice
- NICHD Safe to Sleep: Ways to Reduce the Risk
- AAP: What Should I Do If My Child Is Thinking About Suicide?
Keep the next step clear
Care first. Then an ordinary evening plan.
Your child does not need a label from a search phrase. They need a safe response, someone who listens, and help that fits what is happening.
When those needs are being addressed, the SleepBaby.org homepage offers a free browser-based planning preview for ordinary sleep routines. Use it alongside, never in place of, your child’s medical or mental-health care.






What viewers said10 comments · 4 replies+
Archived comments from the original Baby Sleep Miracle presentation. Not independently verified by SleepBaby.org; individual experiences vary.
Thank you so much for this video! I had no idea about the dangers of baby swings :O
Hi Mary-Ann. I have a question: Is method in any way similar to the ones recommended by Dr Bucknam, Dr. Weissbluth or Dr. Karp? We tried those but none of them help.
Hi Regina, thank you for your question. The short answer is no. The techniques I share in my guide are based on newest scientific research and this is why I have never seen any approach similar to the one I recommend.
This method really works! I tried it on my son Jesus and after just one week he went from waking up more than 5 times a night to waking up just once or twice. You are a lifesaver, Mary-Ann!
I'm truly impressed with how much information you share in your video. And all for free! I can feel that you truly care about mothers like myself, and that's hard to find these days. I have recommended your site to several of my friends already.
Mary-Ann, our child suffers from autism. Is your approach still suited?
Chloe, I made sure my method can be used with any child, even babies who are special like yours. Please note that I'm not a doctor and that I always advice to consult with your physician because nothing is more important than the safety and well-being of your love.
Hallo Mary-Ann, I'm from Germany. Do you have your guide in German?
Hello Heide, we do! Normally you should already see our video in German. If not, please contact our support so they can guide you
Thenk you for your answer, Mary-Ann!
I just completed your approach and I have to say, it worked almost too well. Yes, it took a bit of getting used to with your bedtime routine but the difference is huge. My son George used to take 1 hours to go down and now he's firmly asleep in no more than 10 minutes! You're the best!
It seems I'm the only man watching this video, lol! What you shared about the 'emotional backpack' made immediate sense to me and I can't wait to help my little girl Mila to unpack it!
Hey there, just discovered your site and this really sounds different. Just wanted to say thanks for sharing :)
For everyone who's still thinking about getting Mary-Ann's guide I want to advise you to go ahead. I wasn't sure myself but now I'm so thankful I invested in this program. It made a huge difference in our life as a family and yes, my baby girl does sleep through the night now.