
It is 2:17 a.m. The feed happened. The diaper is clean. You have paced the same strip of floor so many times that it feels like a commute, and your baby is still crying instead of sleeping. Colic can make sleep painfully fragmented, but “colic” should never be used to explain away a baby who may be ill, hungry, in pain, or struggling to feed. First check the baby, then protect the sleep space, then repeat one calm soothing loop. Do not switch to side or stomach sleep, an inclined product, a medicine, or an unproven “colic cure” just because everyone is exhausted.
A colicky baby may sleep in short, messy pieces—but the safety rules do not change
Colic describes a repeated crying pattern in an otherwise well young baby, not a diagnosis you can make from the volume of one terrible night. Babies with a typical colic pattern are generally feeding and growing, look well between episodes, and become content again when the bout passes. The pattern often begins in the first weeks and improves by about 3 to 4 months.
If your baby does not look well between bouts, the cry is new or unusual, feeding has changed, or your instincts say this is different, call the baby’s clinician. If the baby is well and the pattern has already been medically discussed, aim for a repeatable, low-stimulation sequence—not a perfect bedtime.
Call now when the picture is bigger than colic
Call emergency services now if your baby has trouble breathing, turns blue or gray, has a seizure, becomes floppy or unresponsive, is very difficult to wake, or looks seriously ill. Get urgent medical advice for a baby younger than 12 weeks with a temperature of 100.4°F (38°C) or higher.
Also call the baby’s clinician or urgent care promptly for a weak, high-pitched, or clearly unusual cry; a bulging soft spot; repeated or green vomit; poor feeding; fewer wet diapers or other dehydration signs; pain when touched or moved; an injury; unusual sleepiness; poor weight gain; or nonstop crying that remains impossible to console for about 2 hours. A sudden change from your baby’s usual pattern matters even when it does not fit a checklist.
If you are afraid you may shake or hurt your baby: place the baby on the back in an empty crib or bassinet, step into another room briefly, and call someone who can relieve you. Never shake a baby. A few minutes of crying in a safe sleep space is safer than being held by an adult who is losing control.
The moment I stop trying to “win” bedtime with Benjamin
Imagine me—Kacey—in a clearly labeled composite evening with baby Benjamin crying against my chest. I have paced the same hallway, reopened the diaper caddy, rewarmed the same cup of tea, and searched three versions of “colic baby not sleeping.” Nothing is wrong with the effort. The trap is that every failed minute makes the next idea feel more urgent.
In this composite, I say the sentence that changes the room: “I am not trying to make sleep happen right now. I am checking safety, lowering stimulation, and asking for a turn.” A relief adult checks Benjamin’s temperature, reviews his last feed and wet diaper, and sets a handoff timer. I keep him upright while we are both awake, then hand him over before either adult becomes dangerously drowsy. When he finally softens, the transfer is to the same firm, flat, empty bassinet—on his back.
This is a hypothetical editorial composite, not a claim about my or Benjamin’s real family history and not evidence for a treatment. I am using it because the most useful shift is often smaller than a new technique: stop grading the night by minutes asleep and start grading it by whether the baby and caregiver stayed safe.
Use three clocks instead of one
When the only clock you watch is minutes since the baby last slept, almost any product or position can start to look reasonable. I would widen the frame. Track the body clock, the crying clock, and the caregiver clock together. They answer three different questions, and none should be allowed to erase the other two.
The body clock
When was the last effective feed? Has the baby had normal wet diapers? Is there fever, vomiting, breathing trouble, a new rash, swelling, a hair wrapped tightly around a toe, or pain with movement? The body clock asks whether “colic” is hiding a need that requires care.
The crying clock
When did this bout begin? Does it cluster at a similar time on many days? Does your baby look comfortable between episodes? A repeating evening pattern in an otherwise well baby is more compatible with colic than a brand-new all-day cry with poor feeding.
The caregiver clock
How long has the current adult been holding the baby? Is that adult nodding off, shaking with anger, or unable to think clearly? The caregiver clock determines when to hand over, set the baby safely down, or call for help.


What a typical colic pattern does—and does not—look like
Colic is usually discussed when a young infant has recurrent, hard-to-soothe crying without an identified medical cause. The crying may build in the late afternoon or evening, the baby may clench fists, pull up the legs, or turn red, and a bout may resist the soothing that worked yesterday. That resistance is one reason the night can feel so personal. It is not proof that the baby is rejecting you.
The reassuring part of the pattern lives between episodes: the baby returns to a more settled state, feeds adequately, has expected wet diapers, and continues to grow. A baby who remains listless, feeds poorly, vomits repeatedly, seems painful when handled, or cannot be consoled at any point needs assessment rather than a stronger colic routine.
| What you notice | What it may mean | Useful next move |
|---|---|---|
| Crying clusters around a similar evening window; baby appears well between bouts | Compatible with a colic or normal crying-peak pattern after other causes are excluded | Use one soothing loop, document the pattern, and discuss it with the baby’s clinician |
| Crying appears around feeds with coughing, choking, poor intake, forceful vomiting, blood in stool, or poor growth | A feeding, gastrointestinal, allergy, or other medical issue may need evaluation | Call the clinician; do not diagnose reflux or change formula on your own |
| Baby cries when laid down but settles upright in awake arms | Could reflect normal contact preference, trapped air, feeding discomfort, overtiredness, or another cause | Hold upright while awake after a feed if advised, then transfer to a flat back-sleep surface; never use an incline for sleep |
| A new weak, shrill, or unusual cry, fever, breathing change, unusual sleepiness, or pain with touch | Not a pattern to manage as routine colic | Seek urgent medical advice using the safety guidance above |
Do not let the label become a blindfold
A baby can have a known colic pattern and still become sick on a later day. Recheck the body clock whenever the cry changes, the baby’s behavior between bouts changes, or your concern rises. “The pediatrician said colic last week” is context, not a permanent explanation for every future cry.
Run one low-stimulation soothing loop
A long menu is not always helpful at 2 a.m. It encourages you to switch techniques every 20 seconds, which raises stimulation and makes it impossible to tell what the baby is responding to. I prefer a loop that is short enough to remember, gentle enough to repeat, and bounded by a safety check.
Check the basics once
Look at breathing and color. Check temperature when illness is possible. Review the last effective feed, burp, diaper, wet diapers, and whether clothing is too warm or restrictive. Scan fingers and toes for a tightly wrapped hair. If anything points beyond an ordinary crying bout, stop the loop and call.
Lower the room, not the safety standard
Dim practical lights, reduce voices and screens, and choose one steady sound. A quiet “shhh,” a fan-like sound, or low white noise may be easier to process than music that changes constantly. Keep any sound source away from the baby and use the lowest useful volume.
Use contained, awake comfort
Hold the baby skin-to-clothing against your chest, rock gently, walk slowly, or use a warm bath if your baby usually finds it calming. Keep the baby upright during and after feeds while the caregiver is awake if that helps with burping. Avoid vigorous bouncing. Stop any technique that makes the crying or your stress escalate.
Pause before adding another intervention
Give the chosen approach a few calm minutes unless the baby looks unwell. The goal is not to force silence. It is to make the input predictable enough for the baby’s nervous system—and yours—to come down a notch.
Transfer only to a real sleep space
When the baby becomes drowsy or falls asleep, place the baby on the back on a firm, flat, non-inclined crib, bassinet, portable crib, or play-yard mattress with only the fitted sheet. If the transfer fails, return to the loop. Do not substitute a couch, recliner, swing, lounger, car seat outside travel, nursing pillow, or adult bed.
Hand off before you are spent
Switch adults at a preset time rather than after an argument or near-miss. If no relief adult is available, set the baby down safely and take a brief reset. Drink water, breathe, message someone, and return when your hands and voice are steady.

If the baby is otherwise well but the transfer itself is the sticking point, use a separate plan to help a baby settle in a bassinet without changing the safe sleep surface. If the crying tends to start at the threshold of every nap or bedtime, it may also help to look at why crying clusters right before sleep. Those patterns can coexist with colic, but neither link replaces a medical evaluation when the cry or the baby’s condition has changed.
Safe sleep does not bend for colic
The most dangerous advice in an exhausted household is often the advice that works for five quiet minutes. A side-lying position, prone chest nap, inclined lounger, or car-seat sleep may seem to reduce crying. That does not make it a safe place to leave a sleeping infant. The American Academy of Pediatrics recommends the back for every sleep on a firm, flat, non-inclined surface, with the sleep space clear of pillows, loose blankets, bumpers, toys, wedges, and positioners.
Upright holding can be a useful awake soothing position. It stops being an awake hold when the adult’s eyelids are closing. Couches and recliners are especially hazardous places to drift off with a baby. If you feel sleep arriving, transfer the baby to the bassinet or crib even if you expect protest. A safely crying baby on a flat mattress is safer than a quiet baby trapped between a sleeping adult and a cushion.
These may change during the loop
- Which alert caregiver is holding the baby
- Whether you walk, rock, sing, or use low steady sound
- The order of feeding, burping, diapering, and calming based on the baby’s cues
- Whether you pause and call the clinician
These do not change for sleep
- Baby starts every sleep on the back
- Mattress is firm, flat, and non-inclined
- Sleep space is empty except for the fitted sheet
- No unattended sleep in a swing, lounger, sofa, recliner, or adult bed


If your baby protests as soon as the back touches the mattress, you can troubleshoot back-sleeping protests without abandoning back sleep. For a baby whose medical and feeding checks are reassuring but whose nights remain upside down, this guide to what normal newborn nights can look like can help separate developmental sleep organization from the intense crying window.
Feeding discomfort deserves a question, not a home diagnosis
Many colic conversations quickly turn into reflux, gas, formula intolerance, tongue tie, milk-protein allergy, or “not enough milk.” Any of those words may describe a real issue for a particular baby, but crying alone does not distinguish them. Changing formula repeatedly, restricting a breastfeeding parent’s diet, thickening a bottle, adding cereal, or starting a supplement can create new problems and blur the pattern the clinician needs to see.
Bring observations instead of a diagnosis. Note when the crying starts in relation to feeds, whether the baby latches and swallows effectively, how long feeds last, whether there is coughing or choking, the color and force of vomit, stool changes, wet diapers, and growth concerns. A short video of the behavior may help the clinician if it can be recorded without delaying care.
A useful message to the pediatric office
“My baby is ___ weeks old. The crying usually starts around ___ and lasts ___. Between episodes the baby is/is not alert and comfortable. In the last 24 hours there were ___ feeds and ___ wet diapers. I am seeing/not seeing fever, vomiting, breathing changes, blood in stool, pain with touch, or unusual sleepiness. This pattern is new/typical, and tonight my main concern is ___.”
I would not routinely add gripe water, herbal drops, anti-colic drops, probiotics, antihistamines, melatonin, or another medicine to make a colicky baby sleep. Evidence and product quality vary, and an infant dose is not something to improvise. Ask the baby’s clinician about any product before giving it. A prescribed treatment for a diagnosed condition is a separate decision and should be used only as directed.
Protect the adult who is absorbing the crying
Prolonged crying is not merely annoying background noise. It changes breathing, judgment, muscle tension, and impulse control. The National Center on Shaken Baby Syndrome uses the Period of PURPLE Crying framework to explain that crying can peak, come and go unpredictably, resist soothing, and last longer than a caregiver expects. The lesson is not “ignore your baby.” It is “a healthy baby can keep crying despite competent care, so adults need a safety plan before frustration peaks.”
Write the handoff plan during daylight if you can. Name the people you are willing to call. Decide how long one adult holds the shift. Put water and a snack where the on-duty adult can reach them. Keep the safe sleep space ready, not filled with laundry. If you are solo, identify the sentence you will use: The baby is safe. I am allowed to step away for five minutes.
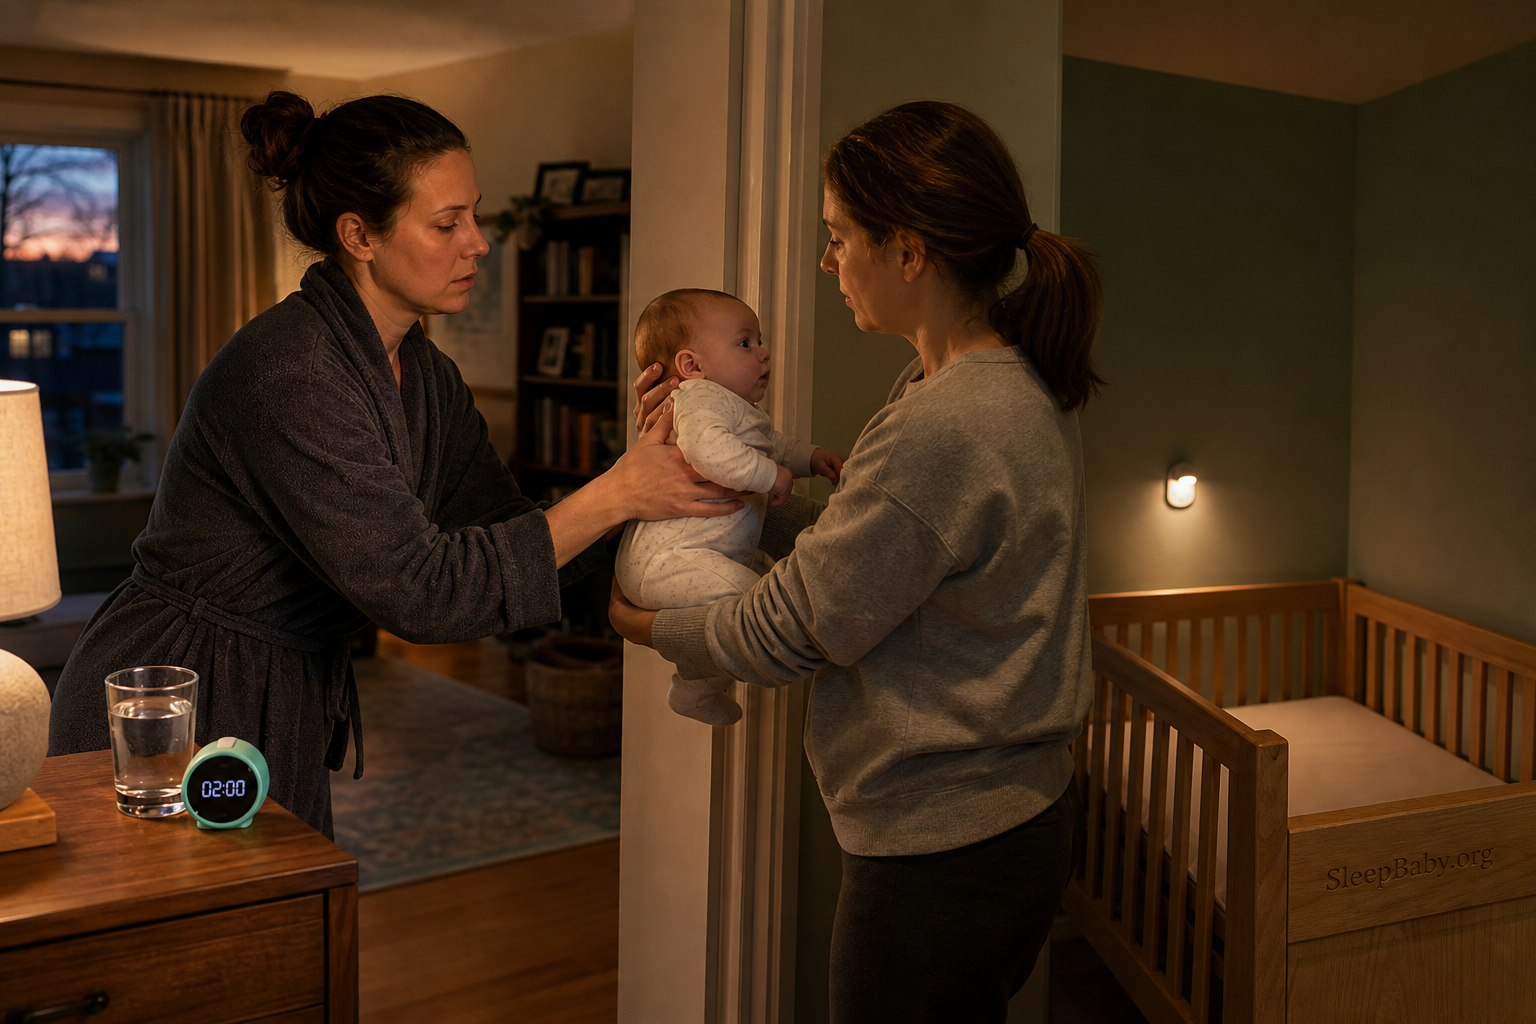

Why crying can continue even when you are doing the right things
This brief Period of PURPLE Crying video from the National Center on Shaken Baby Syndrome gives families a shared language for the crying peak and the safety reason to step away before frustration becomes dangerous.
If the player does not load, watch The Period of PURPLE Crying PSA on YouTube.
What better sleep looks like during the colic weeks
Improvement may not look like a six-hour stretch. It may look like catching the crying window earlier, completing a feed without frantic switching, getting one clean bassinet transfer, or handing off before the room becomes unsafe. Those are not consolation prizes. They are the building blocks of a night that can be repeated.
Keep a tiny log for two or three days, not an elaborate surveillance project. Record feed start, wet diapers, crying-bout start and stop, what the baby was like between bouts, and the longest sleep interval. The purpose is to show a clinician and reduce duplicate guessing—not to prove that you can optimize a newborn.
Call for a routine appointment even without emergency signs if the pattern is hard to manage, the baby is not gaining as expected, you are unsure the feeds are effective, crying continues beyond about 4 months, or your household cannot recover between episodes. Parent wellbeing belongs in the clinical conversation. “We cannot safely keep doing this without help” is useful medical information.
The morning after is part of the plan
After a brutal night, the temptation is to rebuild everything before breakfast: order five remedies, change the feeding plan, lengthen every wake window, and promise that tonight will run on a perfect schedule. I would make the morning smaller. Keep normal feeds unless a clinician has told you otherwise, write down the few observations that matter, and ask for one concrete block of adult rest. A rested caregiver is not cosmetic support; that person is better able to notice a changed cry, complete a safe transfer, and stop before frustration becomes dangerous.
Preserve the facts
Record the longest crying bout, what the baby was like between bouts, feeds, wet diapers, temperature if taken, vomiting or stool changes, and what finally happened. Leave out theories until the clinician hears the pattern.
Preserve the sleep space
Clear the bassinet or crib again. Remove the blanket, nursing pillow, wedge, or lounger that migrated into the room overnight. Resetting the environment in daylight prevents an exhausted shortcut from becoming tonight’s default.
Preserve the people
Ask for a specific shift: “Can you hold the awake baby from 7 to 8 while I sleep?” is easier to answer than “Can you help sometime?” If no one is available, tell the pediatric office that caregiver exhaustion is affecting safety.
A portable sound cue that can follow the soothing loop
The Yogasleep Rohm Portable White Noise Sound Machine fits one exact job in this situation: it gives you a predictable low-stimulation sound while you move from holding, to pacing, to a safe bassinet transfer without keeping a phone in your hand. Its portable format and direct volume controls make more sense for a moving colic shift than an app-heavy fixed nursery hub.
This is not a cure for colic, a sleep guarantee, or a substitute for feeding or medical evaluation. Keep it outside the crib or bassinet, away from the baby, and at the lowest useful volume. Nothing should attach to or sit inside the sleep space. I prefer this kind of narrow-use tool over a swing, wedge, positioner, ingestible remedy, or “smart” fix that changes the safe sleep surface or makes a treatment claim.
See the Yogasleep Rohm on Amazon
As an Amazon Associate, SleepBaby may earn from qualifying purchases.
The night can be hard without being a verdict
Return to that 2:17 a.m. room. The crying may still be loud. The baby may still need to be held again after the transfer. What has changed is the meaning of the moment. You are no longer searching for one trick that proves you understand your baby. You are watching three clocks, protecting the sleep surface, and using a loop that has an end.
I want you to remember the order: look for illness and feeding problems; lower stimulation; soothe while awake; place every sleep on the back on a firm, flat, empty surface; hand off before exhaustion becomes dangerous. If the baby looks unwell or the pattern is different, call. If the baby is well and the colic pattern is familiar, repetition is not failure. It is how you carry both of you through a developmental storm without making the night less safe.
Sources
- NHS. Colic.
- American Academy of Pediatrics, HealthyChildren.org. Crying Baby — Before 3 Months Old.
- American Academy of Pediatrics, HealthyChildren.org. A Parent’s Guide to Safe Sleep.
- American Academy of Pediatrics, HealthyChildren.org. How to Calm a Fussy Baby.
- American Academy of Pediatrics, HealthyChildren.org. Abdominal Pain in Infants: 8 Possible Reasons Your Baby Is Uncomfortable.
- NHS. Soothing a crying baby.
- National Center on Shaken Baby Syndrome. The Period of PURPLE Crying.
Build the plan around the crying window—not another desperate fix
When medical and feeding concerns have been addressed, SleepBaby can help you turn the rest of the night into a workable sequence: who takes the first shift, how the safe transfer happens, what counts as a reset, and where the next stretch of sleep can realistically fit.
Build a calmer plan for the crying window
SleepBaby’s planning support does not diagnose or treat colic and does not replace emergency care or advice from your baby’s clinician.






What viewers said10 comments · 4 replies+
Archived comments from the original Baby Sleep Miracle presentation. Not independently verified by SleepBaby.org; individual experiences vary.
Thank you so much for this video! I had no idea about the dangers of baby swings :O
Hi Mary-Ann. I have a question: Is method in any way similar to the ones recommended by Dr Bucknam, Dr. Weissbluth or Dr. Karp? We tried those but none of them help.
Hi Regina, thank you for your question. The short answer is no. The techniques I share in my guide are based on newest scientific research and this is why I have never seen any approach similar to the one I recommend.
This method really works! I tried it on my son Jesus and after just one week he went from waking up more than 5 times a night to waking up just once or twice. You are a lifesaver, Mary-Ann!
I'm truly impressed with how much information you share in your video. And all for free! I can feel that you truly care about mothers like myself, and that's hard to find these days. I have recommended your site to several of my friends already.
Mary-Ann, our child suffers from autism. Is your approach still suited?
Chloe, I made sure my method can be used with any child, even babies who are special like yours. Please note that I'm not a doctor and that I always advice to consult with your physician because nothing is more important than the safety and well-being of your love.
Hallo Mary-Ann, I'm from Germany. Do you have your guide in German?
Hello Heide, we do! Normally you should already see our video in German. If not, please contact our support so they can guide you
Thenk you for your answer, Mary-Ann!
I just completed your approach and I have to say, it worked almost too well. Yes, it took a bit of getting used to with your bedtime routine but the difference is huge. My son George used to take 1 hours to go down and now he's firmly asleep in no more than 10 minutes! You're the best!
It seems I'm the only man watching this video, lol! What you shared about the 'emotional backpack' made immediate sense to me and I can't wait to help my little girl Mila to unpack it!
Hey there, just discovered your site and this really sounds different. Just wanted to say thanks for sharing :)
For everyone who's still thinking about getting Mary-Ann's guide I want to advise you to go ahead. I wasn't sure myself but now I'm so thankful I invested in this program. It made a huge difference in our life as a family and yes, my baby girl does sleep through the night now.