The monitor is moving. Your baby may still be sleeping.
Why it can look like your baby never goes into a deep sleep
The screen glows. An eyelid flutters, one hand jumps, a tiny groan comes through the speaker, and you are halfway out of bed before the picture settles again. If your baby seems restless through every nap, the most likely explanation is not that deep sleep is missing. Young babies spend a large share of sleep in active sleep, when twitching, sucking motions, facial expressions, little sounds, and uneven-looking breathing can all happen. They repeatedly move between this active state and quieter, stiller sleep.
I would judge the whole baby, not the amount of motion on a monitor: Are there calmer stretches? Does your baby wake and feed normally, breathe comfortably, have their usual wet diapers, and behave like themselves when awake? Movement alone cannot tell us that a baby is getting poor-quality sleep. A sudden change plus breathing trouble, blue or gray color, unusual limpness, extreme difficulty waking, poor feeding, dehydration, or fever in a young infant changes the answer and needs prompt medical attention.

The movements that make sleep look lighter than it is
Adults tend to picture “real sleep” as a motionless face, slow breathing, and absolute silence. Newborn sleep did not receive that memo. The American Academy of Pediatrics describes two broad newborn sleep states: active sleep, which is REM sleep, and quiet sleep, which is non-REM sleep. During active sleep, a baby may twitch, jerk an arm or leg, move beneath closed eyelids, suck, smile, grimace, whimper, or briefly fuss. Breathing can look less regular than it does during quiet sleep.
Quiet sleep is the easier state to recognize. The face is calmer, the body is relatively still, and breathing is steadier. But “quieter” does not mean “the only useful sleep,” and active sleep is not a defective waiting room outside deep sleep. It is a normal part of infant sleep architecture.
I think this distinction matters because the phrase deep sleep often becomes shorthand for “the kind of sleep I can trust.” The private question is rarely about sleep-stage terminology. It is: Is my baby actually resting, or am I missing something wrong? The answer comes from patterns, health, and context—not from trying to label every minute through a camera.
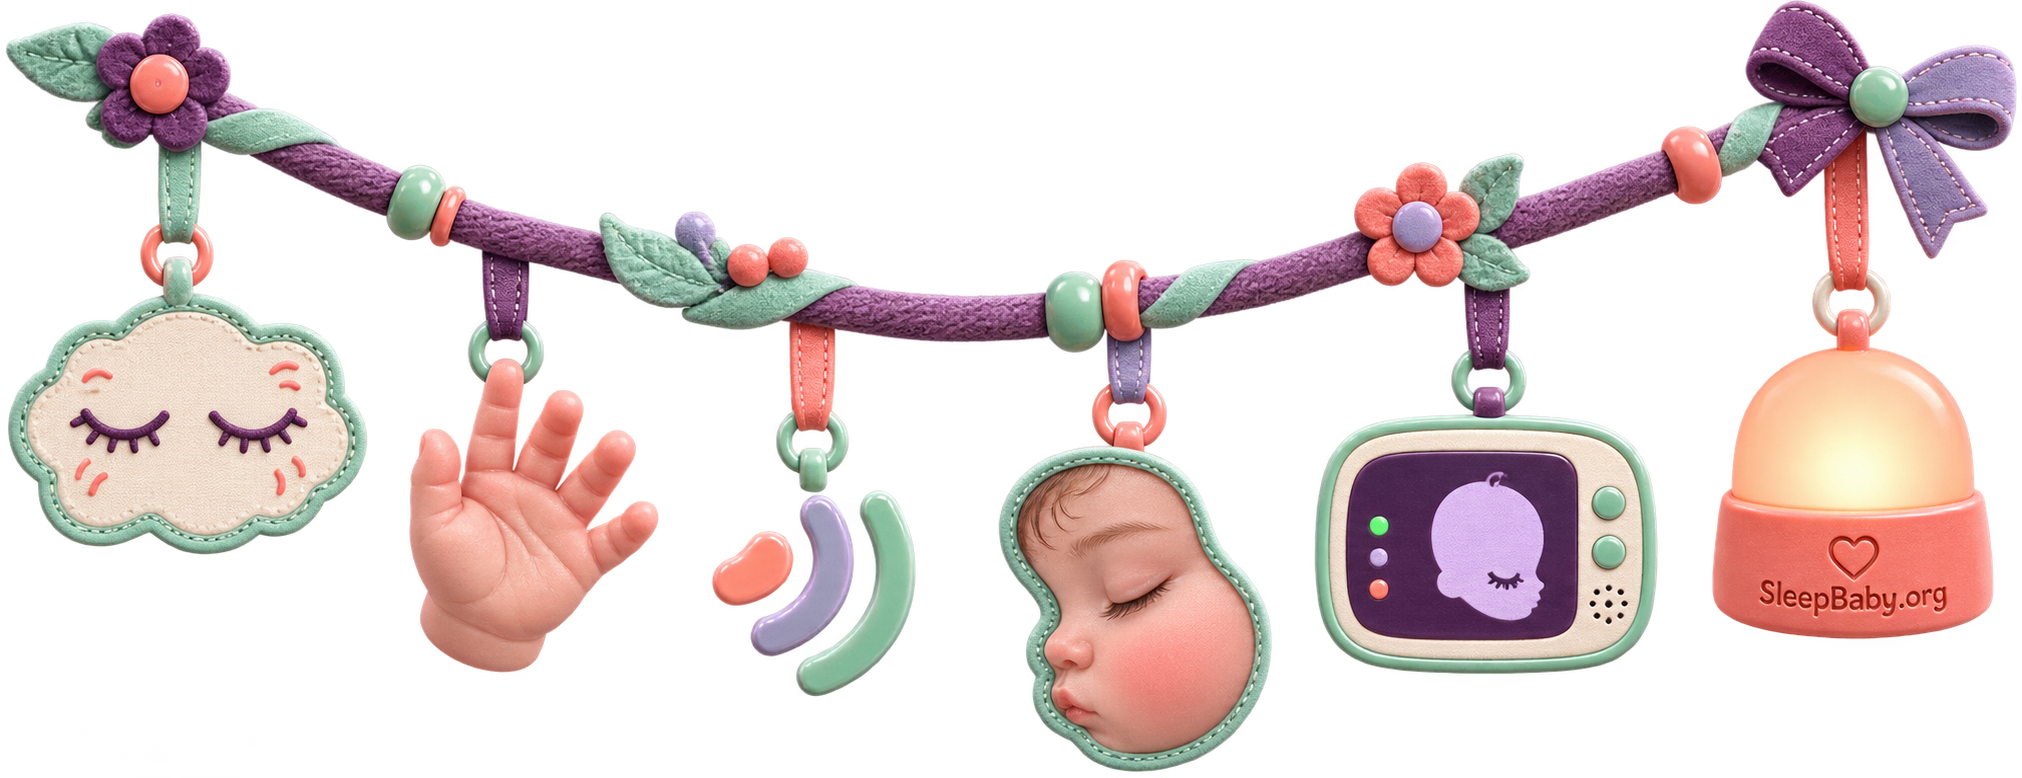
A visible-state decoder
Active sleep
You may see: closed eyes with eyelid flutter, brief twitches, sucking motions, tiny facial changes, soft noises, or movement that comes and goes.
Useful response: keep watching briefly if color and breathing look comfortable. Many moments settle without help.
Quiet sleep
You may see: a stiller face and body, closed eyes, and slower, more regular breathing.
Useful response: let sleep continue. You do not need to prove how long this stage lasts.
Waking or awake
You may see: eyes opening and staying open, purposeful movement, feeding cues, or a cry that grows rather than fades.
Useful response: respond to the need in front of you—feeding, comfort, a diaper, temperature, illness, or connection.
Body clues that are not a sleep-stage puzzle
Act promptly for: struggling to breathe, ribs pulling in, blue or gray color, a prolonged breathing pause, unresponsiveness, or abnormal limpness. Call emergency services for severe or immediate danger.
SleepBaby.org visual guide: identify the state, then choose the smallest safe response.
When the monitor turns every eyelid flutter into a question
A clearly labeled hypothetical Kacey-and-Benjamin scene: Imagine me at 1:38 a.m., watching Benjamin’s eyelids move on the monitor while one fist lifts and drops against the mattress. I lean toward the screen as though better posture might reveal his exact sleep stage. A small sound comes through. I reach for the door—and then he goes still, breathes evenly, and keeps sleeping. The monitor has once again produced twelve seconds of programming and somehow made it feel like a season finale.
That imagined moment is not evidence about any real child. It shows the judgment problem: intervening during a normal transition can finish waking a baby who was moving between sleep states on their own. I do not want parents to ignore a baby who needs them. I want us to separate movement from need.
The detail I would watch is what happens next. Does the motion fade while the eyes remain closed? Does the sound stay brief? Does breathing look comfortable and color remain normal? Or does the baby become fully alert, increasingly upset, hungry, hot, cold, congested, in pain, or otherwise unlike themselves? One pathway invites a pause. The other invites care.

Use a pause–observe–respond sequence
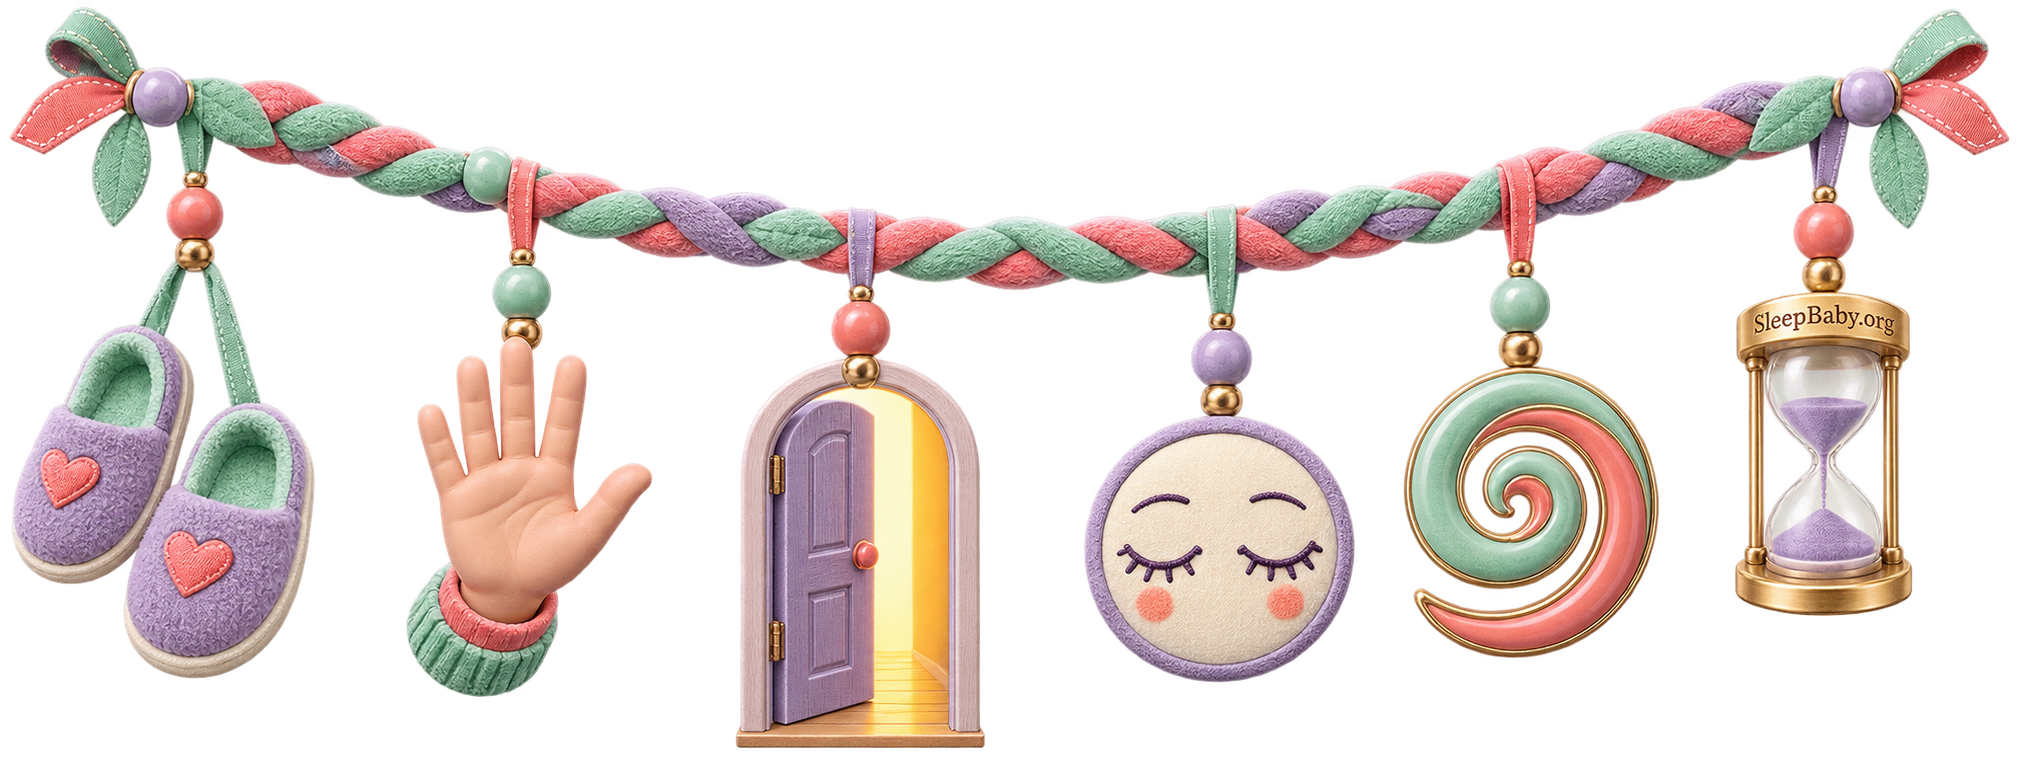
When a baby’s sleep is noisy, the most useful tool is not a stopwatch for deep sleep. It is a small decision sequence that keeps safety first and prevents every flutter from becoming a household event.
Pause
If your baby is safely positioned and there is no urgent body clue, give the moment a little room. This is not a rigid timer. It may be only long enough to take one breath and look carefully.
Observe
Look for closed versus open eyes, a brief versus building sound, comfortable versus labored breathing, normal color, and whether movement fades or becomes purposeful.
Respond
If the moment passes, let sleep continue. If your baby wakes or needs care, respond. If the body looks wrong, skip sleep troubleshooting and seek medical help.
I like this sequence because it does not ask a tired parent to become a sleep-lab technician. It asks only: Is this passing, building, or concerning? That is a question you can actually answer at night.
If your baby regularly moves from a stir into a full wake every hour, the issue may be less about whether deep sleep exists and more about repeated waking. Our guide to separating a noisy sleep transition from a wake that actually needs help takes that next question further.
Age changes what sleep looks like
Newborn sleep is distributed across day and night, and early cycles are shorter and less adult-like. Active sleep occupies a large share of that time. As the nervous system matures, sleep organization changes. A parent may begin to notice longer quiet stretches, more predictable timing, or different patterns around feeds and naps—but not on a perfectly smooth schedule.
This is why I would not compare a six-week-old’s monitor footage with an older baby who has settled into longer nighttime blocks. Nor would I compare two babies of the same age as though they were appliances running the same software. Age offers context; your baby’s baseline supplies the more useful comparison.
For the developmental view, see how active and quiet sleep change across the first year. That age-by-age guide is more useful than applying one fixed cycle length to every baby and setting an alarm for the minute “deep sleep” is supposed to arrive.
What to track for three ordinary sleep periods
This is a short observation tool, not a diagnostic log. Stop tracking if it makes you more anxious.
- How sleep began: feeding, rocking, being placed down awake, or another ordinary route.
- What you noticed: eyelid flutter, one startle, grunting, repeated crying, or a full wake.
- What happened next: settled without help, needed feeding, needed comfort, or stayed awake.
- Whole-baby context: normal feeds, wet diapers, alert periods, breathing, color, illness, and any sudden change.
The aim: replace “all night” with a small, factual pattern. Three observations often tell you more than three hours of monitor vigilance.
SleepBaby.org observation tool: notice the transition without turning the night into surveillance.

What common sleep noises can—and cannot—tell you
Grunting is the sound that sends many parents searching first. A brief grunt during closed-eyed sleep can happen as a baby shifts, stretches, passes gas, or moves through active sleep. It does not automatically mean pain or breathing trouble. The sound matters less than the work around it. A baby whose chest and belly move comfortably, whose color stays normal, and who settles again is showing a different picture from a baby whose nostrils flare, ribs pull inward, color changes, or breathing looks genuinely hard.
Squeaks, snorts, and congested-sounding little noises can also be surprisingly loud in young babies. Their airways are small, and ordinary secretions can sound dramatic through a monitor microphone. I would still look directly if the sound is new, persistent, or paired with feeding trouble, fever, retractions, color change, or distress. A microphone amplifies noise; it cannot examine a baby.
Small cries can occur in sleep too. The useful distinction is duration and direction. One brief cry followed by relaxed silence may be part of a transition. Crying that repeats, builds, or comes with open eyes and purposeful movement is more likely to be a true wake. You do not have to withhold comfort to prove which one it is. A short pause simply gives you more information before you choose.
Twitches are often easiest to misread because they can look so abrupt. Brief, irregular jerks limited to sleep may occur during active sleep. Movements that also happen while awake, repeat in a concerning rhythm, come with unusual eye or breathing changes, or leave your baby difficult to wake deserve clinician review. If you are unsure, note when the movement happens and what the baby is like immediately before and after. That context is more valuable than naming it yourself.
Read the whole moment, not one signal
| What catches your attention | What makes a passing transition more likely | What changes the response |
|---|---|---|
| A grunt or squeak | Eyes stay closed, color is normal, breathing is comfortable, sound fades | Persistent noisy breathing, retractions, color change, feeding difficulty, or distress |
| A twitch or startle | Brief, irregular, happens during sleep, baby settles | Repeated concerning movement while awake, altered responsiveness, or breathing change |
| A short cry | One or two sounds, relaxed face returns, no building wake | Crying grows, eyes stay open, feeding or comfort cues appear |
| Uneven-looking breathing | Brief variation without struggle or color change | Prolonged pause, gasping, marked effort, blue or gray color, or unresponsiveness |
SleepBaby.org comparison: direction and context matter more than one isolated sound.
Feeding, waking, and growth tell you more than monitor stillness
When parents say a baby “never sleeps deeply,” sometimes the real concern is that the baby wakes so often they wonder whether any sleep is restorative. In early infancy, waking to feed is expected, and protecting feeding is more important than trying to lengthen sleep by delaying a needed feed. Follow the feeding plan you received for your baby, especially for a newborn, a premature baby, or a baby with weight-gain concerns.
The reassuring pattern is broader: your baby wakes enough to feed effectively, has the expected wet diapers, has alert periods appropriate for age, and is growing along the path their clinician is following. If sleepiness makes feeding consistently difficult, your baby cannot be awakened for feeds as instructed, or diapers and weight raise concerns, call the pediatric clinician. “Deep sleeper” should never become an explanation for a baby who is too sleepy to eat.
At the other end, frequent visible movement does not prove that milk supply, formula, or solids are inadequate. Hunger is one possible reason for a full wake, but it is not the explanation for every facial movement during closed-eyed sleep. I would look for actual feeding cues and the larger feeding pattern rather than adding feeds solely because the camera caught a twitch.
Illness can temporarily make sleep noisier, more fragmented, or unusually heavy. Congestion, discomfort, fever, vomiting, and breathing changes all alter the context. A sudden pattern during illness deserves a different level of attention than the same familiar squeaks your healthy baby has made for weeks.
Three well-meant fixes I would skip
Trying to force stillness
Holding a pacifier in place, repeatedly repositioning a safely sleeping baby, or rushing in for every sound can add stimulation during a normal transition. If there is no safety or care need, stillness does not have to be manufactured. The aim is sleep, not a perfect monitor image.
Chasing a sleep-stage score
Consumer devices may estimate sleep from movement or other signals, but an estimate cannot diagnose whether an infant reaches deep sleep. A low score can turn ordinary variation into a nightly performance review. If the baby’s health or sleep quality truly concerns you, bring the observable pattern to a clinician rather than trying to optimize a proprietary number.
Changing the sleep surface
It can be tempting to add cushioning, elevation, a nest, or weight because a baby looks unsettled on a flat surface. Do not. The safe surface is intentionally firm, flat, level, and empty. A product that makes the picture look calmer is not an acceptable trade for a safer sleep environment.
I would also resist changing bedtime, wake windows, feeding, white noise, clothing, and the entire routine on the same night. If your baby is healthy and the issue is simply restless-looking sleep, there may be nothing to fix. When a real pattern needs troubleshooting, one measured change teaches you more than six simultaneous experiments.
Questions parents ask after watching a restless sleeper
Should I pick my baby up when they grunt with closed eyes?
Not automatically. First check breathing, color, position, temperature, and whether the sound is passing or building. If your baby stays asleep and comfortable, a brief grunt may need no response. If they wake, show feeding cues, cry increasingly, or seem unwell, respond.
Can a baby be in deep sleep and still move?
Sleep states are not perfectly visible from outside, and a brief movement does not let us label the exact stage. Quiet sleep is generally stiller than active sleep, but the practical point is that movement does not prove restorative sleep is absent.
Why does my baby seem quieter when held?
Contact may reduce visible startling or help a baby settle, but an adult holding a sleeping infant must remain fully awake. If you might fall asleep, move baby to their own safe sleep surface. Couches and armchairs are especially dangerous places to doze with an infant. A quieter contact sleep is not evidence that the crib prevents deep sleep.
Do daytime naps contain active sleep too?
Yes. Active and quiet sleep are not reserved for nighttime. Keep the same safe-sleep setup for every nap, and use the same body-first observation rather than assuming daytime movement means the nap has ended.
When should I mention this at a routine appointment?
Bring it up if you remain worried, if sleep seems to interfere with feeding or daytime alertness, if movements also occur while awake, or if the pattern has changed. A concise description—when it happens, how long it lasts, whether eyes are open, and what breathing and behavior look like afterward—helps the clinician answer more precisely.
Restless-looking sleep does not change safe-sleep rules
A baby who looks active does not need a softer mattress, a positioner, an incline, a weighted sleep product, loose bedding, or a different sleep position to “help” them get deeper. For every sleep, place your baby on their back on a firm, flat, level surface designed and approved for infant sleep. Keep the sleep space empty. Follow current guidance about room-sharing and stop swaddling when your baby shows signs of trying to roll.
Do not use a swing, car seat, lounger, or other sitting device as a routine sleep space. If a baby falls asleep there, move them to an appropriate sleep surface as soon as practical. A peaceful-looking picture cannot make an unsafe setup safe.
Safe sleep, every time
Keep the observation plan inside a safe sleep space
The American Academy of Pediatrics reviews the sleep-space basics that remain in place whether your baby is twitching through active sleep or lying quietly.
Takeaway: a safe, empty, flat sleep space is the foundation. Watching a transition never replaces it.
When to stop watching the sleep pattern and get help
This section is deliberately commerce-free. Sleep stages are not the question when a baby’s body looks unwell.
Get emergency help now
- Your baby is struggling to breathe, the skin pulls in around the ribs, or breathing stops for a prolonged period.
- Lips, tongue, face, or skin look blue or gray.
- Your baby is unresponsive, abnormally limp, or cannot be awakened normally.
- You believe there is immediate danger. Call emergency services.
Contact your baby’s clinician promptly
- Sleepiness comes with poor feeding, repeated vomiting, fewer wet diapers, or other dehydration signs.
- A young infant has a fever, or your clinician has given you an age-specific fever threshold.
- Your baby is much harder to wake than usual, has unusual movements while awake, or shows a sudden persistent change from baseline.
- You have concerns about growth, breathing, illness, or development—even if a short video does not capture the problem.
If you can safely record a brief episode that concerns you, it may help a clinician see what you mean. But do not delay urgent care to make a recording, and do not rely on a consumer monitor to rule out a medical problem.


A monitor can support the pause—without pretending to measure deep sleep
If your practical problem is that every sound sends you into the room, a basic video view can help you check whether eyes remain closed and a movement settles. For this exact job, I would choose the VTech VM819 Video Baby Monitor. Its value here is straightforward: video answers “Is my baby still asleep?” better than sound alone, without asking you to wear an app on your wrist, subscribe to a sleep score, or infer a sleep stage from a graph.
I prefer that fit over a breathing sock, a sleep-stage tracker, or a soothing gadget because none of those products should decide whether a baby is medically safe, and soothing is not the problem this section is solving. The persuasive reason to buy is modest but real: seeing a closed-eyed stir fade can spare an unnecessary room entry and preserve a sleep transition that was already working.
Boundary: this is an observation tool, not a medical monitor. It cannot diagnose sleep, monitor breathing medically, prevent SIDS, replace direct checks, or make an unsafe sleep setup safe. Use it according to the manufacturer’s instructions and keep cords completely out of a child’s reach.
As an Amazon Associate, SleepBaby may earn from qualifying purchases.
Choose the smallest response that fits the moment
By now, that glowing screen should mean something different. A moving hand is not proof of missing deep sleep. A grunt is not automatically a request. A still body is not the only sign that sleep “counts.” Your baby can move through active and quiet sleep many times, and the transitions may be visible.
My practical rule is simple: protect the sleep space, look at the whole baby, and choose the smallest response that fits. Sometimes that response is feeding or comfort. Sometimes it is calling the pediatrician. Sometimes it is standing in the hallway for ten more seconds while the eyelids stop fluttering and the room becomes quiet again.
The goal is not to become less attentive. It is to make your attention more useful.
For the nights when every sound feels like a decision
Turn monitor-watching into a calmer sleep plan
When you can tell a passing transition from a wake that needs you, the hallway feels less like a command center. SleepBaby helps you build the next layer: routines, timing, and responses that fit your actual baby and household.
Sources
- American Academy of Pediatrics, HealthyChildren.org. Stages of Newborn Sleep.
- Raising Children Network. Newborn sleep: what to expect.
- NHS Best Start in Life. Understanding your baby.
- American Academy of Pediatrics, HealthyChildren.org. Getting Your Baby to Sleep.
- NHS. Helping your baby to sleep.